
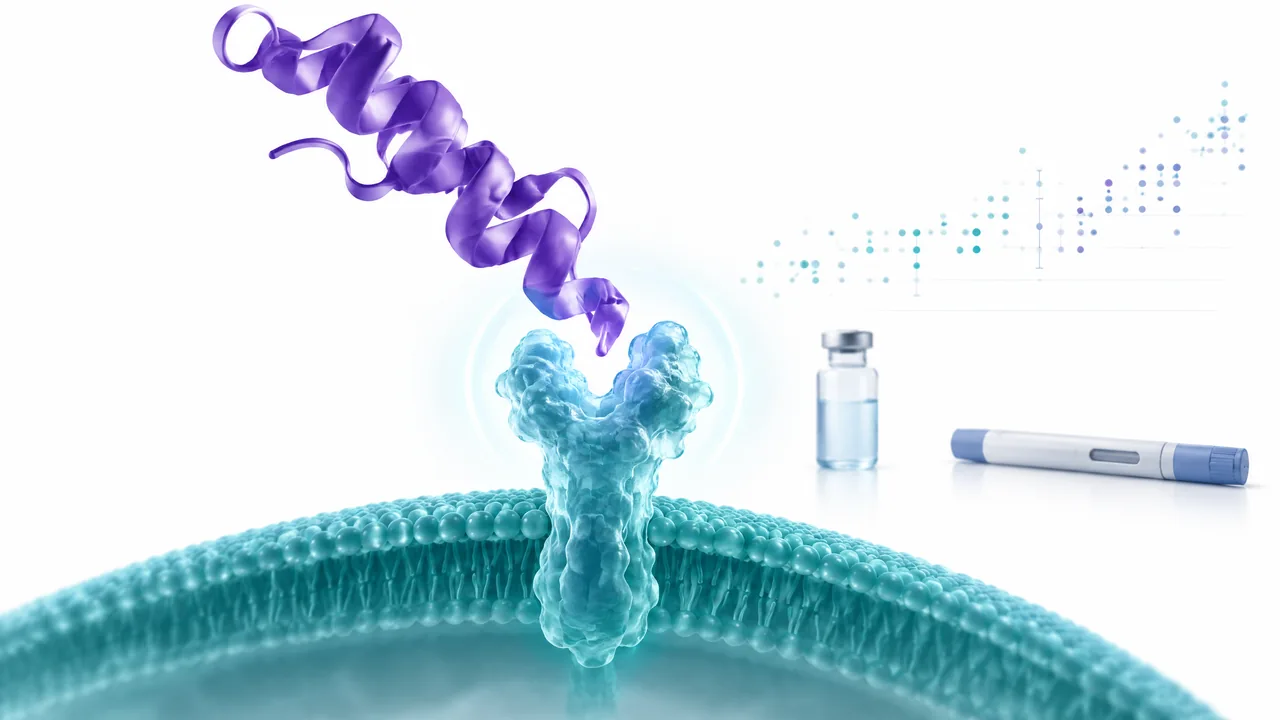
What is Semaglutide?
Semaglutide is a synthetic, long-acting glucagon-like peptide-1 (GLP-1) analogue and GLP-1 receptor agonist. It is a peptide medicine, not a small molecule, cosmetic topical ingredient, hormone replacement product, or a generic ‘research peptide’ category. Its design includes two amino-acid substitutions relative to human GLP-1 and a lysine-26 derivatisation that increases albumin affinity.
Evidence-grounded Australian educational material on semaglutide as an approved GLP-1 peptide medicine. It distinguishes registered formulations from unapproved vial products, explains what the clinical trials actually tested, and places benefits, risks and unresolved questions in their specific study settings.
Identity: a GLP-1 peptide medicine, not a generic vial category
Semaglutide is a purpose-designed GLP-1 analogue. The discovery study reports two substitutions relative to human GLP-1—Aib at position 8 and Arg at position 34—and modification at lysine 26. The fatty-acid/linker design increases albumin affinity and was selected to prolong exposure; in that preclinical pharmacology programme, the molecule was the candidate taken forward for once-weekly development. This chemical identity matters because it is not interchangeable with the body’s native GLP-1 or with an unspecified product marketed as a ‘GLP-1 peptide’. [1]
In Australia, semaglutide is not investigational-only. TGA material identifies Ozempic and Wegovy as the semaglutide-containing products approved for supply, and identifies them as prescription-only medicines. Ozempic is included in the Australian Register of Therapeutic Goods (ARTG) for adult type 2 diabetes, while Wegovy is approved for chronic weight management as an adjunct to reduced-energy eating and increased physical activity in adults who meet its BMI and comorbidity criteria. These are formulation- and indication-specific approvals, not a blanket endorsement of every use or every container labelled semaglutide. [2] [3] [4]
Molecular pathway: what is established and what is not
The direct molecular action is GLP-1 receptor agonism. The Australian Wegovy Product Information describes semaglutide as a GLP-1 analogue made by recombinant-DNA technology, while the discovery work measured GLP-1 receptor affinity and increased albumin affinity. In clinical pharmacology, GLP-1 receptor agonism is associated with glucose-dependent effects on insulin secretion and delayed gastric emptying; the latter is clinically relevant enough that the TGA now highlights a potential aspiration risk during general anaesthesia or deep sedation. [1] [3] [9]
A receptor-level description should not be turned into a simplistic promise. Weight change, glycaemic change and cardiovascular outcomes emerge from whole-person treatment in particular populations, alongside background care and, in weight-management trials, lifestyle intervention. The cited trials demonstrate clinical differences between randomised groups; they do not isolate one universal receptor-to-weight-loss pathway or establish that an individual will have the group-average response. [5] [6] [7] [8]
Human evidence for obesity or overweight: the STEP 1 model
STEP 1 was a double-blind, randomised, placebo-controlled trial in 1,961 adults with obesity, or overweight plus at least one weight-related coexisting condition, without diabetes. Participants were assigned in a 2:1 ratio to subcutaneous semaglutide 2.4 mg or placebo for 68 weeks, with lifestyle intervention in both groups. This is therefore strong evidence for that specific non-diabetes, lifestyle-supported model; it is not a trial of self-directed treatment, unregulated vials, or people with every possible clinical profile. [5]
At week 68, mean body-weight change was −14.9% with semaglutide and −2.4% with placebo, an estimated treatment difference of −12.4 percentage points. Weight reduction of at least 5% occurred in 86.4% and 31.5% of the respective groups. Nausea and diarrhoea were the most common adverse events, and gastrointestinal events led to treatment discontinuation in 4.5% of the semaglutide group versus 0.8% of the placebo group. A mean and a threshold proportion describe outcomes across trial participants; neither predicts an individual’s benefit or tolerability. [5]
Type 2 diabetes and cardiovascular-outcomes models are different questions
SUSTAIN 6 studied a different population and endpoint: 3,297 people with type 2 diabetes on standard care, 83.0% of whom had established cardiovascular disease, chronic kidney disease or both. Over 104 weeks, participants were randomised to once-weekly semaglutide 0.5 mg or 1.0 mg, or placebo. The primary composite of cardiovascular death, nonfatal myocardial infarction or nonfatal stroke occurred in 6.6% of the semaglutide group and 8.9% of placebo, with a hazard ratio of 0.74 (95% confidence interval 0.58 to 0.95). The trial was designed for cardiovascular safety and enrolled a high-risk diabetes cohort, so its result should not be transplanted unchanged to people without diabetes or baseline cardiovascular disease. [7]
Its safety signal also needs the same context. SUSTAIN 6 reported more diabetic-retinopathy complications with semaglutide than placebo (hazard ratio 1.76, 95% confidence interval 1.11 to 2.78), while fewer people had new or worsening nephropathy; gastrointestinal adverse events were a leading reason for discontinuation. The Australian PI accordingly advises monitoring people with a history of diabetic retinopathy, particularly when glucose control improves rapidly. This is a reason for clinical assessment, not evidence that every person taking semaglutide will develop an eye complication. [4] [7]
SELECT addressed yet another model: 17,604 adults aged at least 45 years with established cardiovascular disease and BMI of at least 27, but no diabetes. With mean follow-up of 39.8 months, a first cardiovascular death, nonfatal myocardial infarction or nonfatal stroke occurred in 6.5% with semaglutide 2.4 mg and 8.0% with placebo (hazard ratio 0.80, 95% confidence interval 0.72 to 0.90). Permanent discontinuation due to adverse events was more frequent with semaglutide, 16.6% versus 8.2%. This supports cardiovascular benefit in the studied high-risk population; it does not prove primary prevention benefit in everyone with overweight or obesity. [8]
What continuation and withdrawal research can—and cannot—say
STEP 4 tested maintenance after a response-enriched lead-in rather than simply comparing new starters. All 902 entrants received semaglutide during a 20-week run-in; 803 who had reached the 2.4-mg maintenance dose were then randomised to continue semaglutide or switch to placebo for 48 more weeks, with lifestyle intervention in both groups. By design, the randomised comparison applies to people who completed that lead-in and reached the maintenance dose, not to everyone who might consider starting treatment. [6]
From week 20 to week 68, mean body weight changed by −7.9% in the continuation group and +6.9% after switch to placebo. This supports continued treatment producing additional loss and the placebo-switch group regaining weight on average in this trial setting. It does not establish one inevitable stopping trajectory, a universal duration of treatment, or an appropriate individual management plan. [6]
Risks and uncertainty: reading the label alongside the trials
Gastrointestinal effects are central to semaglutide’s risk profile. The Australian Wegovy PI warns that nausea, vomiting and diarrhoea can contribute to dehydration and deterioration of renal function, including postmarketing reports of acute kidney injury or worsening chronic renal failure. It also identifies acute pancreatitis as an observed class concern, advises caution in people with a history of pancreatitis, and notes increased hypoglycaemia risk when semaglutide is used with insulin or a sulfonylurea. Those warnings are not a checklist for self-management; they are reasons to use a prescriber and pharmacist who can assess the person and their other medicines. [4]
Delayed gastric emptying has a separate procedural implication. In 2025, the TGA required a class-wide precaution after reports of pulmonary aspiration during general anaesthesia or deep sedation despite reported pre-procedure fasting. A person using a GLP-1 receptor agonist should tell the treating team and anaesthetist before a procedure; decisions about fasting, timing or treatment changes belong with those clinicians rather than a generic online schedule. [9]
Important evidence gaps remain. The Wegovy PI says there is limited experience in people aged 75 years or older and no experience in New York Heart Association class IV heart failure; it also states that safety and efficacy below age 18 years had not been studied in that PI. Trial eligibility criteria, monitored follow-up and sponsor funding mean that trial estimates should be applied with attention to population, duration and real-world suitability. [4] [5] [6] [8]
Australian regulatory context and product integrity
Australian readers should separate the active ingredient from the product. The TGA says Ozempic and Wegovy are prescription-only GLP-1 receptor agonist medicines, and that Ozempic’s ARTG indication is type 2 diabetes; advertising it for weight loss is illegal. Wegovy has a distinct chronic-weight-management indication. Brand names, legal advertising rules and approved indications are not clinical advice, but they help distinguish a documented registered medicine from promotional language. [2] [3]
A research-supplier vial, telehealth-marketed ‘semaglutide-like’ preparation or an unregistered online product is not interchangeable with the registered medicine. The TGA states that compounded semaglutide-like products are unapproved therapeutic goods that it has not evaluated for quality, safety or efficacy; they may differ in strength and ingredients. It also warns that unknown websites may supply products with undisclosed or harmful ingredients and notes detection of counterfeit semaglutide imports. Neither the STEP nor SUSTAIN/SELECT trials validate dilution, storage, injection, substitution or combination protocols for such products. [5] [7] [8] [10]
How to compare related substances and read a semaglutide headline
Semaglutide is a selective GLP-1 receptor agonist. Tirzepatide is a different peptide medicine with dual GIP/GLP-1 receptor agonism, and the TGA treats it as a separate prescription medicine and approved product category. A headline comparing medicines is only as useful as its comparator, assigned dose, population and outcome: SUSTAIN 6 was a high-risk type 2 diabetes cardiovascular-safety trial, whereas STEP 1 studied obesity or overweight without diabetes and SELECT studied people with established cardiovascular disease without diabetes. Cross-trial percentages are not head-to-head rankings. [3] [5] [7] [8] [9]
Before interpreting a result, ask who was enrolled, what the control group received, how long follow-up lasted and what outcome was prespecified. Then check discontinuation and exclusions. STEP 4’s withdrawal result, for example, follows a semaglutide lead-in and randomises only people who reached the maintenance dose; SELECT’s cardiovascular result applies to people with pre-existing cardiovascular disease. These details turn a marketing-style number into evidence with a usable boundary. [6] [8]
Questions readers ask
Is semaglutide actually a peptide?
Yes. Semaglutide is a modified GLP-1 analogue, designed as a long-acting peptide GLP-1 receptor agonist. It is not a small molecule, a topical ingredient or a naturally occurring hormone supplied unchanged. [1] [4]
Is semaglutide approved in Australia?
Yes, in the registered prescription formulations Ozempic and Wegovy. TGA material identifies Ozempic for adult type 2 diabetes and Wegovy for chronic weight management under its approved BMI and comorbidity criteria. Approval is product- and indication-specific. [2] [3] [4]
Do the STEP 1 results mean everyone will lose about 15% of body weight?
No. The −14.9% figure was the mean change at 68 weeks in STEP 1 participants receiving semaglutide 2.4 mg plus lifestyle intervention; participants did not have diabetes and met defined entry criteria. Individual response, adverse effects and discontinuation vary. [5]
What does the evidence say about stopping semaglutide?
In STEP 4, people who had completed a semaglutide lead-in and then switched to placebo regained weight on average over the following 48 weeks, while those continuing semaglutide lost more weight on average. It is useful maintenance evidence, but not a personalised forecast or a self-directed stopping protocol. [6]
Why is an online or ‘research-use’ semaglutide vial not the same as Ozempic or Wegovy?
The TGA has evaluated the registered medicines, whereas it states that compounded semaglutide-like products are unapproved and have not been evaluated for quality, safety or efficacy. Unknown online products may also have undisclosed ingredients or be counterfeit. [4] [10]
What remains uncertain
The key efficacy studies answer different questions in different populations: STEP 1 excluded diabetes, SUSTAIN 6 enrolled a high-risk type 2 diabetes population, SELECT required established cardiovascular disease and STEP 4 randomised only people who completed a semaglutide lead-in and reached maintenance dose. No single percentage is a general-purpose individual forecast. [5] [6] [7] [8]
Several pivotal reports were funded by Novo Nordisk, and authors include company employees and/or report industry relationships. Randomisation and blinding where used are important protections, but sponsorship, duration, eligibility and treatment discontinuation remain relevant when judging generalisability. [5] [6] [7] [8]
This record intentionally does not supply a personal dosing, titration, reconstitution, storage, injection, substitution, stopping or blend protocol. These cannot be inferred safely from trial summaries and are especially inappropriate for unregistered or research-supplier products; the current Product Information and an Australian prescriber or pharmacist are the appropriate sources for product-specific care. [3] [4] [10]
References and further reading
- [1] Discovery of the Once-Weekly Glucagon-Like Peptide-1 (GLP-1) Analogue Semaglutide. Medicinal-chemistry, receptor-affinity and nonclinical pharmacokinetic programme, including cell systems, rodents and miniature pigs; the mini-pig model measured a 46.1-hour intravenous plasma half-life and 63.6-hour mean residence time after subcutaneous dosing.
- [2] Advertising Ozempic and GLP-1 receptor agonists is prohibited. TGA regulatory and advertising guidance, last updated 11 March 2025.
- [3] Medicines containing GLP-1 and dual GIP/GLP-1 receptor agonists. TGA Medicines Safety Update published 3 June 2025, describing Australian marketed products and class-wide Product Information warning changes.
- [4] Australian Product Information – Wegovy (semaglutide) solution for injection. TGA-approved Product Information accompanying the Wegovy Australian Public Assessment Report finalised 4 September 2024.
- [5] Once-Weekly Semaglutide in Adults with Overweight or Obesity. STEP 1: 68-week, double-blind, randomised, placebo-controlled trial of 1,961 adults with obesity or overweight plus a weight-related condition, without diabetes; semaglutide 2.4 mg once weekly plus lifestyle intervention versus placebo plus lifestyle intervention.
- [6] Effect of Continued Weekly Subcutaneous Semaglutide vs Placebo on Weight Loss Maintenance in Adults With Overweight or Obesity: The STEP 4 Randomized Clinical Trial. STEP 4: phase 3 randomised-withdrawal trial at 73 sites in 10 countries; 902 adults entered a 20-week semaglutide run-in and 803 reaching 2.4 mg were randomised to continue semaglutide or switch to placebo for 48 weeks, with lifestyle intervention.
- [7] Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes. SUSTAIN 6: 104-week, randomised, placebo-controlled cardiovascular-outcomes trial of 3,297 people with type 2 diabetes on standard care; semaglutide 0.5 mg or 1.0 mg once weekly versus placebo.
- [8] Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. SELECT: multicentre, double-blind, randomised, placebo-controlled, event-driven superiority trial of 17,604 adults aged 45 years or older with established cardiovascular disease, BMI at least 27 and no diabetes; semaglutide 2.4 mg once weekly versus placebo.
- [9] Medicines containing GLP-1 and dual GIP/GLP-1 receptor agonists. TGA Medicines Safety Update published 3 June 2025; this source is intentionally repeated as a citation anchor for the anaesthesia/deep-sedation warning.
- [10] Compounding safety information: semaglutide-like products. TGA safety and regulatory advisory published 15 December 2023 on compounded semaglutide-like products and counterfeit risks.


